Hospital and Medical Device Threat Taxonomy
Taxonomies › Hospitals and medical devices
This is the reference for the Critical Condition card game: every card’s threat, the mitigation principle a sound design follows, design measures, and mappings to STRIDE, LINDDUN, CAPEC, CWE, ATT&CK, EMB3D and MDS2.
It covers the hospital and the medical devices in it, on it and around it: implants and their programmers, body-worn and home-use devices, patient monitors (ECG, SpO2, blood pressure, heart rate), ventilators and other life support, infusion pumps and pharmacy systems, X-ray, CT, MRI and radiotherapy, the laboratory and clinical software. Around them sit the systems that run care: records, integration, networks, clinical and emergency communications, the building, suppliers, identity and continuity.
It is written for a mixed table: device manufacturers, clinical engineering, hospital IT and security, integrators, estates teams and emergency services. It is jurisdiction-neutral. Hospitals are critical infrastructure, and the adversary may be a ransomware group, a state preparing for a crisis, an insider, or nobody at all: a faulty update or a failed link. What sets hospitals apart is the consequence. A design flaw that costs another business money can cost a patient their life, and the hospital can’t close while it recovers.
The two decks and the Trumps
Critical Condition is played with two decks, and each deck plays on its own. Each has its suits, the ten structural hazards as Trumps, a quick-reference card and a taxonomy card whose QR code links to this page.

The Patient (116 cards) is what touches the patient: implants, body-worn devices, monitors, life support, medication, imaging, the laboratory and clinical software. It’s the deck for device makers and clinical engineering.

The Hospital (129 cards) is what runs care: records, integration, networks, clinical and emergency communications, the building, suppliers, identity and downtime. It’s the deck for hospital IT, estates and suppliers.
Trumps are the ten structural hazards of hospitals and medical devices as a whole, and both decks carry them. To cover a whole system, play the two decks one after the other.
The ID format
Every entry has the ID printed on its card: the game prefix, the suit and the rank, joined by hyphens, such as CRI-PM-K (the King of Patient Monitoring) or CRI-TR-4 (Trump 4). The hyphens make each ID a single searchable token. Ranks are frozen: an entry added later between two ranks takes an intermediate value, such as CRI-PM-3.1, so no published ID ever changes. Every entry on these pages has an anchor, so #cri-pm-k links straight to it.
In the game, ranks follow severity, Ace high to 2. In the taxonomy the ID is a stable reference, not a severity: rate each finding on its merits in your own system.
The suits
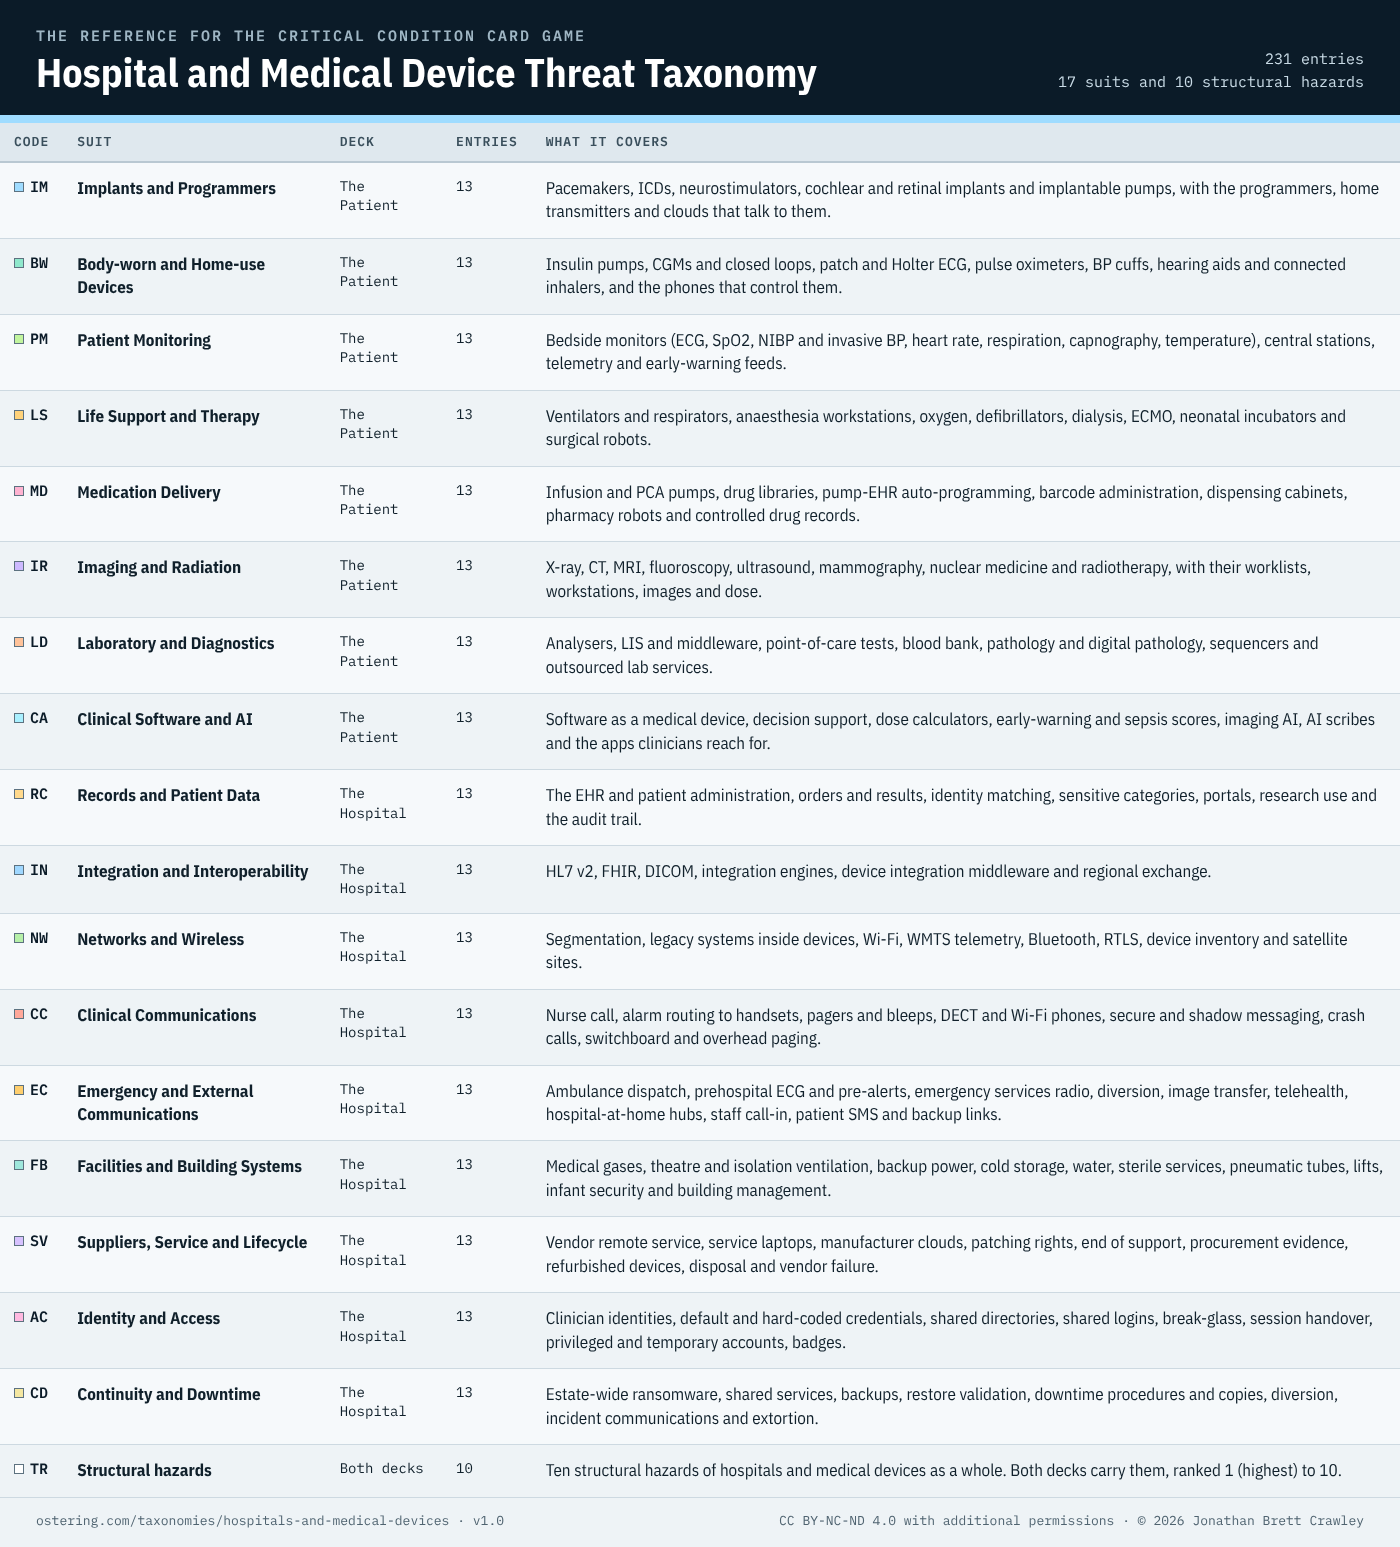
The table gives every suit at a glance: its code, its deck, how many entries it holds and what it covers. The list under it links to each suit’s page, where every entry is set out in full.
The Patient
- 01 · Implants and Programmers (IM): 13 threats. Pacemakers, ICDs, neurostimulators, cochlear and retinal implants and implantable pumps, with the programmers, home transmitters and clouds that talk to them.
- 02 · Body-worn and Home-use Devices (BW): 13 threats. Insulin pumps, CGMs and closed loops, patch and Holter ECG, pulse oximeters, BP cuffs, hearing aids and connected inhalers, and the phones that control them.
- 03 · Patient Monitoring (PM): 13 threats. Bedside monitors (ECG, SpO2, NIBP and invasive BP, heart rate, respiration, capnography, temperature), central stations, telemetry and early-warning feeds.
- 04 · Life Support and Therapy (LS): 13 threats. Ventilators and respirators, anaesthesia workstations, oxygen, defibrillators, dialysis, ECMO, neonatal incubators and surgical robots.
- 05 · Medication Delivery (MD): 13 threats. Infusion and PCA pumps, drug libraries, pump-EHR auto-programming, barcode administration, dispensing cabinets, pharmacy robots and controlled drug records.
- 06 · Imaging and Radiation (IR): 13 threats. X-ray, CT, MRI, fluoroscopy, ultrasound, mammography, nuclear medicine and radiotherapy, with their worklists, workstations, images and dose.
- 07 · Laboratory and Diagnostics (LD): 13 threats. Analysers, LIS and middleware, point-of-care tests, blood bank, pathology and digital pathology, sequencers and outsourced lab services.
- 08 · Clinical Software and AI (CA): 13 threats. Software as a medical device, decision support, dose calculators, early-warning and sepsis scores, imaging AI, AI scribes and the apps clinicians reach for.
The Hospital
- 09 · Records and Patient Data (RC): 13 threats. The EHR and patient administration, orders and results, identity matching, sensitive categories, portals, research use and the audit trail.
- 10 · Integration and Interoperability (IN): 13 threats. HL7 v2, FHIR, DICOM, integration engines, device integration middleware and regional exchange.
- 11 · Networks and Wireless (NW): 13 threats. Segmentation, legacy systems inside devices, Wi-Fi, WMTS telemetry, Bluetooth, RTLS, device inventory and satellite sites.
- 12 · Clinical Communications (CC): 13 threats. Nurse call, alarm routing to handsets, pagers and bleeps, DECT and Wi-Fi phones, secure and shadow messaging, crash calls, switchboard and overhead paging.
- 13 · Emergency and External Communications (EC): 13 threats. Ambulance dispatch, prehospital ECG and pre-alerts, emergency services radio, diversion, image transfer, telehealth, hospital-at-home hubs, staff call-in, patient SMS and backup links.
- 14 · Facilities and Building Systems (FB): 13 threats. Medical gases, theatre and isolation ventilation, backup power, cold storage, water, sterile services, pneumatic tubes, lifts, infant security and building management.
- 15 · Suppliers, Service and Lifecycle (SV): 13 threats. Vendor remote service, service laptops, manufacturer clouds, patching rights, end of support, procurement evidence, refurbished devices, disposal and vendor failure.
- 16 · Identity and Access (AC): 13 threats. Clinician identities, default and hard-coded credentials, shared directories, shared logins, break-glass, session handover, privileged and temporary accounts, badges.
- 17 · Continuity and Downtime (CD): 13 threats. Estate-wide ransomware, shared services, backups, restore validation, downtime procedures and copies, diversion, incident communications and extortion.
Both decks
- 18 · Structural hazards (TR): 10 hazards. Ten structural hazards of hospitals and medical devices as a whole. Both decks carry them, ranked 1 (highest) to 10.
Where each suit sits
The map places each suit by how close it sits to the patient. The Patient deck’s suits are on, in and at the bedside, with the departments and clinical software around them. Further out come the hospital’s systems, then the building, then the outside world: the ambulance service, other hospitals, the patient at home and the vendors. The Trumps aren’t placed, because they apply everywhere.
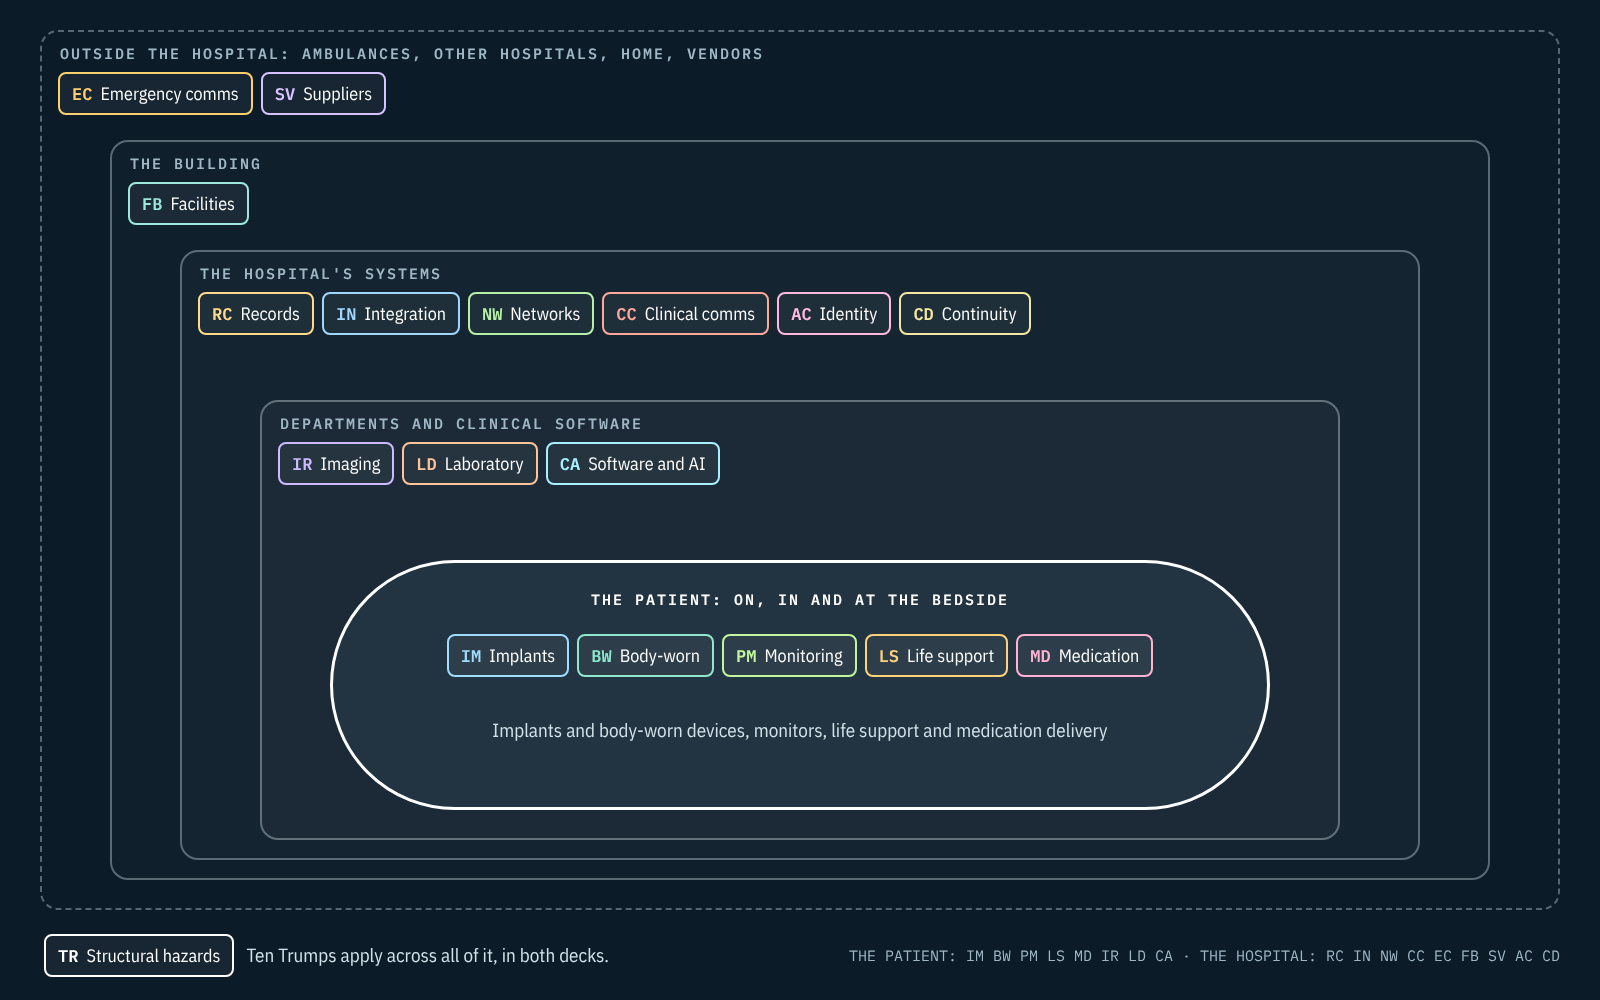
Use the map to pick suits for a session. Start from the part of the system you are designing, then add the suits on either side of it: most threats in this taxonomy cross one of those boundaries.
How to read an entry
Every entry has the same shape. The card carries the ID, the title, the threat and three prompts. The taxonomy adds what the card has no room for: the principle a sound design follows, the design measures and the mappings.
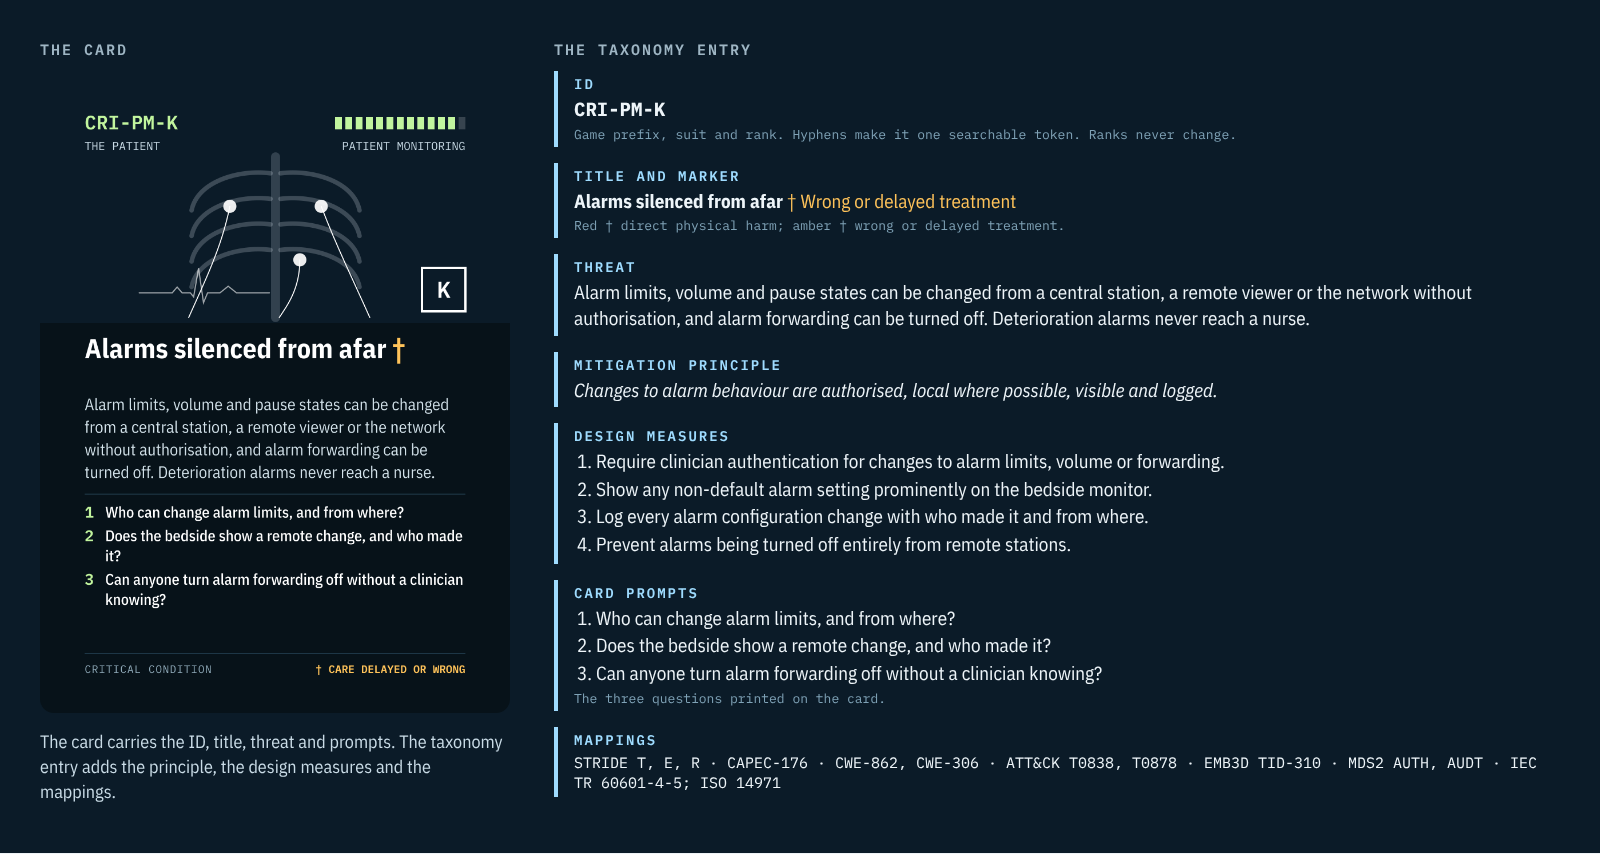
Every entry has the same parts:
- ID and title, as printed on the card.
- Threat: the design weakness and what it leads to, written against the system you are reviewing.
- Principle: what a sound design does about it, in one sentence.
- Design measures: three concrete measures, four where one more was needed. Other designs can meet the principle too.
- Card prompts: the three questions the card asks the table.
- Mappings: STRIDE; LINDDUN where there is a privacy angle; CAPEC; CWE; ATT&CK (Enterprise, or ICS for building and device control); MITRE EMB3D for embedded devices; the MDS2 security capabilities, the main one first; and the standards that address the entry directly. A blank means nothing fitted well.
The two † markers
Two markers flag a consequence for patient safety. 156 of the 231 entries carry one:
- Red †, direct harm (55 entries): the threat can itself injure or kill a patient: a wrong dose delivered, therapy changed, life support stopped, a radiation overdose, a gas or power failure. In the game, a red † finding is not accepted without the person who owns clinical safety for the system in the room.
- Amber †, wrong or delayed treatment (101 entries): the harm comes through information, communication or service failure: a missed alarm, a wrong result, a stale record, a delayed ambulance. An amber † finding needs a clinical lead’s sign-off before it is accepted.
Where the other taxonomies take over
This taxonomy picks the others up only where they become a route into patient care, or a consequence for it:
- Care Assistant Threat Taxonomy: Monitoring of the elderly, babies and mental health patients at home, and the carer relationship.
- Critical Infrastructure (Cyberwarfare) Threat Taxonomy: The grid, water, gas, fuel and logistics that feed the hospital, against a state adversary.
- Software Factory Threat Taxonomy: The build pipelines, registries and update channels of the vendors who make the software.
- AI and Agentic Systems Threat Taxonomy: AI agents, retrieval, tools and MCP servers, wherever they run.
- Email Infrastructure Threat Taxonomy: The machinery that delivers email, including the mail a hospital sends and receives.
Seen in the wild
Each of these public cases illustrates one or more entries. Attribution is given only where an official body made it.
- Medtronic Conexus telemetry, 2019 (CRI-IM-A, CRI-IM-4). US government advisories warned that the Conexus radio protocol used by Medtronic implantable defibrillators, clinic programmers and home monitors had no authentication or encryption, so someone nearby could read or change device settings. Sources: CISA: ICS Medical Advisory ICSMA-19-080-01.
- Abbott (St. Jude Medical) pacemakers, 2017 (CRI-IM-K). The FDA approved a firmware update for about 465,000 radio-enabled Abbott pacemakers in the US to stop unauthorised reprogramming; patients had to visit a clinic to have it applied, weighing a small risk of update failure. Sources: Help Net Security: Patients with St. Jude pacemakers called in for firmware update; CSO: 465,000 Abbott pacemakers vulnerable to hacking need a firmware fix.
- Argus II retinal implant, 2020 (CRI-IM-8, CRI-SV-4, CRI-TR-2). Second Sight phased out its Argus II retinal implant and, after laying off most staff in March 2020, could no longer support its more than 350 recipients; patients were left with implants that could not be repaired and, in one case, could not get an MRI without the maker’s input. Sources: IEEE Spectrum: Their bionic eyes are now obsolete and unsupported.
- Medtronic MiniMed insulin pumps, 2019 (CRI-BW-A). The FDA warned that certain older Medtronic MiniMed insulin pumps could be reached over their radio link by someone nearby and their settings changed; Medtronic recalled them and offered replacements, as the pumps could not be updated. Sources: Infosecurity: Insulin pumps recalled by FDA for cybersecurity risks; Becker’s: Medtronic recalls insulin pumps that can be wirelessly hacked.
- SweynTooth Bluetooth flaws, 2020 (CRI-BW-8, CRI-BW-7, CRI-NW-7, CRI-SV-3). The FDA warned that SweynTooth flaws in Bluetooth Low Energy chips used in pacemakers, glucose monitors, insulin pumps and other devices could let someone nearby crash a device, stop it working or bypass security. Sources: RAPS: FDA warns of cybersecurity vulnerabilities in pacemakers and other BLE devices; HPN: FDA informs about potential vulnerabilities in medical devices with Bluetooth Low Energy.
- MDhex, GE patient monitoring, 2020 (CRI-PM-A, CRI-PM-9). CISA published six vulnerabilities (MDhex) in GE Healthcare CARESCAPE telemetry servers, central stations and related patient monitoring products, including hard-coded credentials, that could let an attacker change alarm settings or make devices unusable. Sources: Help Net Security: MDhex vulnerabilities open GE patient monitoring devices to attackers; Computer Weekly: NHS alerted to severe vulnerabilities in GE health equipment.
- URGENT/11, 2019 (CRI-PM-9, CRI-MD-7, CRI-NW-10, CRI-SV-3). The FDA warned that 11 vulnerabilities in IPnet, a third-party network stack inside several embedded operating systems, could let attackers take over or crash medical devices and hospital network equipment, and that manufacturers might not know their products contained it. Sources: Healthcare IT News: URGENT/11, FDA issues alert.
- Contec CMS8000 patient monitors, 2025 (CRI-PM-8). CISA and the FDA warned that Contec CMS8000 patient monitors made hidden connections to a hard-coded internet address, could download and run unverified files, and sent patient data in plain text when a patient was connected; with no fix available, CISA advised unplugging them. A researcher later argued it was more likely insecure design than deliberate backdoor. Sources: CISA: Fact sheet, Contec CMS8000 contains a backdoor; The Hacker News: CISA and FDA warn of critical backdoor in Contec CMS8000.
- Hospira Symbiq infusion pumps, 2015 (CRI-MD-K). The FDA advised hospitals to stop using Hospira Symbiq infusion pumps because they could be accessed remotely over the hospital network and their dosing changed. Sources: MDDI: FDA, stop using infusion pump vulnerable to hacking.
- Elekta cloud outage, 2021 (CRI-IR-K, CRI-SV-Q, CRI-CD-K). Ransomware hit Elekta’s first-generation US cloud service for radiation oncology software, and about 170 US health systems were affected; some cancer centres could not treat patients for over a week because treatment programming was held in the cloud. Sources: Compliancy Group: Healthcare vendor ransomware attack, 170 health systems hit; Yale Daily News: YNHHS pauses radiotherapy treatment for six days.
- DICOM files carrying malware, 2019 (CRI-IR-10, CRI-IN-J, CRI-EC-9). Cylera researchers showed that the DICOM file format allows an image file to also be a working Windows executable, so malware could hide inside medical images protected as patient data (CVE-2019-11687). Sources: NVD: CVE-2019-11687; GovInfoSecurity: Researchers, malware can be hidden in medical images.
- WannaCry and the NHS, 2017 (CRI-IR-9, CRI-NW-A, CRI-NW-K, CRI-SV-J, CRI-AC-Q, CRI-CD-A). WannaCry ransomware disrupted at least 81 of England’s 236 NHS trusts and infected 595 GP practices; the NAO estimated over 19,000 appointments were cancelled, and some trusts diverted ambulances. Sources: NAO: Investigation, WannaCry cyber attack and the NHS; GOV.UK: Foreign Office Minister condemns North Korean actor for WannaCry attacks.
- Open PACS servers, 2019 (CRI-IR-5, CRI-IN-J, CRI-NW-J). Greenbone found about 590 imaging archive (PACS) servers reachable on the internet without protection, exposing records of about 24 million patients and hundreds of millions of images; an update later counted over a billion images. Sources: Help Net Security: Confidential data of 24.3 million patients discovered online; HIPAA Journal: Exposed medical image total rises to 1.19 billion.
- Synnovis pathology attack, London, 2024 (CRI-LD-Q, CRI-CD-K, CRI-CD-10, CRI-TR-6). Ransomware at Synnovis, pathology provider to King’s College Hospital and Guy’s and St Thomas’, led to thousands of postponed operations and appointments and an appeal for O-type blood donors. In June 2025 King’s confirmed a patient had died unexpectedly during the attack, with a long wait for a blood test result among the contributing factors; the local care board reported 170 patients harmed, mostly low harm. Sources: The Register: Qilin ransomware attack on NHS supplier contributed to patient fatality; Digital Health: Patient death linked to cyber attack on NHS pathology provider.
- Change Healthcare, 2024 (CRI-RC-K, CRI-CD-2, CRI-TR-6). Ransomware at Change Healthcare, which handles about one in three US health transactions, left many providers and pharmacies unable to process claims and prescriptions for weeks; the data of about 192.7 million people was taken. Sources: Becker’s: Change Healthcare data breach toll reaches 192.7 million; Fierce Healthcare: UnitedHealth estimates 190M people impacted.
- NHS Dumfries and Galloway, 2024 (CRI-RC-K). A ransomware group stole data from NHS Dumfries and Galloway, claiming 3 TB, and published clinical data on patients to pressure the health board; the board said records were not altered and care continued. Sources: Help Net Security: NHS Scotland confirms ransomware attackers leaked patients’ data; Digital Health: NHS Dumfries and Galloway working with NCSC after 3TB data leak.
- Vastaamo psychotherapy records, Finland, 2020 (CRI-RC-Q, CRI-TR-8). Therapy records of about 36,000 patients of the Vastaamo psychotherapy centre were stolen in 2018 and 2019; in October 2020, after the company refused to pay, patients were extorted individually. A Finnish court convicted the attacker in April 2024 and the appeal court upheld the conviction in 2025. Sources: Wikipedia: Vastaamo data breach; AP via NY1: Finnish hacker gets prison for accessing psychotherapy records.
- Leaking Beeps, 2016 (CRI-CC-10). Trend Micro research showed that pager messages sent by US hospitals were unencrypted and could be read with cheap radio equipment, exposing patient names, diagnoses and treatment details. Sources: Trend Micro: Leaking Beeps, unencrypted pager messages in the healthcare industry; Trend Micro: Are pagers leaking your patients’ PHI?.
- Advanced and NHS 111, 2022 (CRI-EC-A). Ransomware at software supplier Advanced disrupted the Adastra system used by NHS 111 and out-of-hours services, and exposed data on about 80,000 people. The UK Information Commissioner fined Advanced £3.07 million in March 2025. Sources: ICO: Software provider fined £3m following 2022 ransomware attack.
- University Hospital Düsseldorf, 2020 (CRI-EC-K, CRI-CD-8). Ransomware took down systems at University Hospital Düsseldorf and it stopped taking emergency admissions; a woman sent to a hospital in another city died. Prosecutors opened a homicide inquiry but closed it, concluding her condition alone caused her death and the delay did not affect the outcome. Sources: MIT Technology Review: A patient has died after ransomware hackers hit a German hospital; Born’s Tech and Windows World: ransomware at Uniklinik Düsseldorf not responsible for death.
- Ascension, 2024 (CRI-EC-K, CRI-CD-A, CRI-CD-10). A ransomware attack took Ascension’s electronic health records offline across its hospitals, staff worked on paper and some ambulances were diverted; data on about 5.6 million people was taken. Sources: BleepingComputer: Ascension health data of 5.6 million stolen in ransomware attack.
- PwnedPiper pneumatic tubes, 2021 (CRI-FB-8). Armis disclosed nine vulnerabilities in Swisslog Translogic pneumatic tube system stations, used by thousands of hospitals to move samples and drugs, including unsigned firmware updates that could let an attacker take over stations. Sources: The Register: PwnedPiper flaws in Swisslog pneumatic tube systems; Health-ISAC: Armis discovers 9 vulnerabilities in hospital infrastructure.
- Conti attack on Ireland’s HSE, 2021 (CRI-AC-Q, CRI-CD-A, CRI-CD-3). Conti ransomware encrypted about 80% of the Health Service Executive’s IT environment and about 700 GB of data was taken; the HSE shut its national IT down and took around four months to recover fully. PwC’s independent post-incident review was published in December 2021. Sources: HSE: Conti cyber attack on the HSE, full report (PwC); HHS HC3: Lessons learned from the HSE cyber attack.
- CrowdStrike update outage, 2024 (CRI-CD-7). A faulty CrowdStrike security update crashed Windows computers worldwide; hospitals lost systems for hours and some, such as Mass General Brigham, cancelled non-urgent surgeries and visits. Sources: STAT: Hospitals cancel appointments in global tech outage; WBUR: Mass General Brigham cancels non-urgent surgeries.
Mappings
The table shows how far each framework reaches into each suit: how many of its entries map to CAPEC, CWE, ATT&CK, EMB3D and LINDDUN, its most common STRIDE categories, the MDS2 capabilities a buyer should check first, and how many entries carry each † marker.
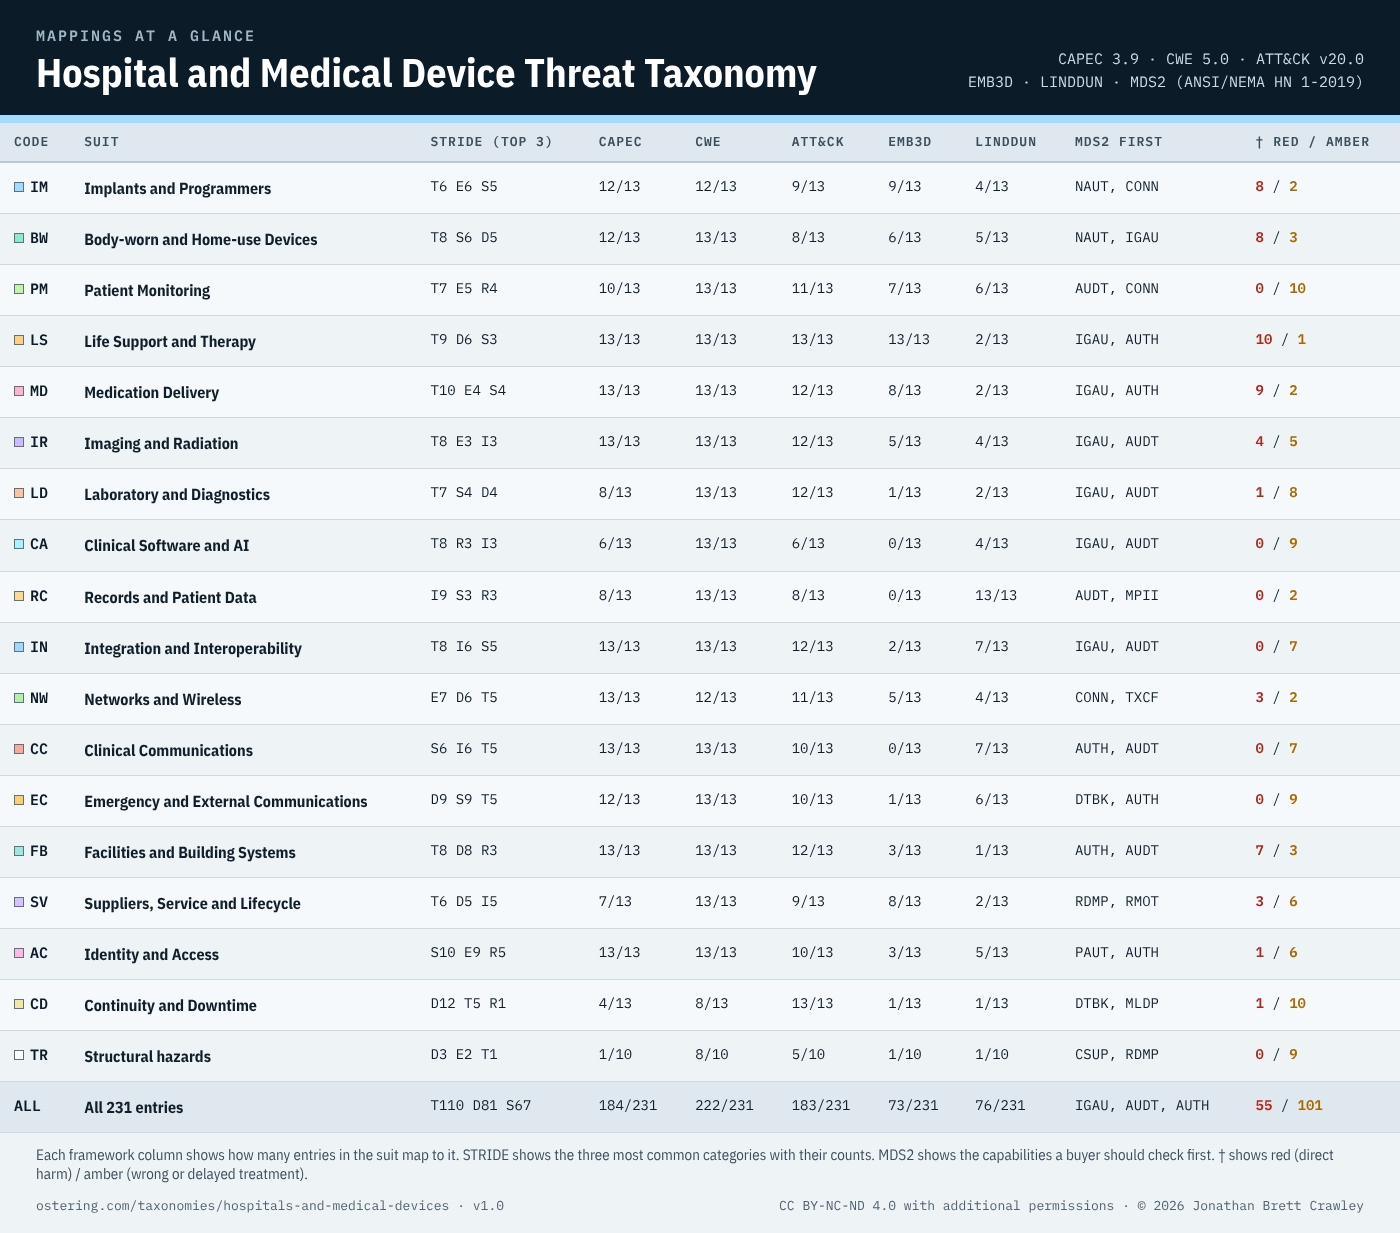
A few things stand out:
- EMB3D is strongest at the bedside. All 13 Life Support and Therapy entries map to it, and 9 of 13 implant entries. It has nothing for clinical software, records or clinical communications, because those threats aren’t in embedded devices.
- LINDDUN concentrates in the records. All 13 Records and Patient Data entries have a privacy mapping, against 1 or 2 in most device suits.
- CAPEC is thinnest where care meets operations. It covers only 4 of 13 Continuity and Downtime entries and 1 of the 10 structural hazards, because those threats are about how a hospital recovers and how it is organised, not about an attack on a component.
- The red † clusters in the device suits. Life Support, Medication Delivery, Implants and Body-worn Devices carry 35 of the 55 direct-harm entries.
Across the 231 entries, the STRIDE counts are Tampering 110, Denial of service 81, Spoofing 67, Information disclosure 63, Elevation of privilege 54, Repudiation 41 (an entry can carry more than one). 184 map to CAPEC 3.9, 222 to CWE 5.0, 183 to ATT&CK v20.0, 73 to MITRE EMB3D and 76 to LINDDUN. The MDS2 capabilities a buyer should check first are IGAU (62), AUDT (57), AUTH (52). 55 carry the red † for direct harm and 101 the amber † for wrong or delayed treatment.
Every ID was checked against MITRE’s own data: ATT&CK Enterprise and ATT&CK for ICS from the v20.0 release (October 2026), CAPEC 3.9, MITRE EMB3D, and CWE 5.0 (28 October 2026). Revoked and deprecated entries were excluded, and only CWEs whose mapping usage is Allowed or Allowed-with-Review were used. MDS2 codes follow ANSI/NEMA HN 1-2019. Each suit page has its own mapping table.
Downloads
| File | Format | What it’s for | Size |
|---|---|---|---|
| hospitals-and-medical-devices-threat-taxonomy.pdf | Read and print: landscape, a section per suit, with the licence on the first pages. | 2.0 MB | |
| hospitals-and-medical-devices-threat-taxonomy.xlsx | Excel | Work with it: a sheet per suit, an all-entries sheet and a licence sheet. | 247 KB |
| hospitals-and-medical-devices-threat-taxonomy.skos.jsonld | SKOS (JSON-LD) | Linked data: a W3C SKOS concept scheme, one concept per entry. | 512 KB |
| hospitals-and-medical-devices-threat-taxonomy.stix.json | STIX 2.1 | Security tools: attack patterns, courses of action and groupings per suit. | 1.2 MB |
Licence
© 2026 Jonathan Brett Crawley. This taxonomy is licensed under the Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International licence (CC BY-NC-ND 4.0), with the additional permissions below. You can share the whole taxonomy freely for non-commercial purposes, unchanged and with credit.
| Use | Permission needed? |
|---|---|
| Sharing the whole taxonomy non-commercially (OWASP, universities, conferences, individuals) | No |
| Threat modeling with it, including for paying clients | No |
| Internal use and training inside any organisation | No |
| Quoting entries, with credit, in paid courses, reports and talks | No |
| Shipping the taxonomy in a product: a tool’s built-in library, a printed deck, a reprint for sale | Yes, ask me |
Additional permissions. In addition to the rights the licence gives, and whether or not the use is commercial, the copyright holder grants you permission to:
- use the taxonomy to threat model systems you build, operate or assess, including for paying clients;
- use it internally, and for training, inside any organisation;
- quote individual entries, with credit, in paid courses, reports, findings and talks.
Any other commercial use, including shipping the taxonomy or a substantial part of it in a product (a tool’s built-in library, a printed deck, a reprint for sale), needs written permission. Ask me on LinkedIn.
Credit: “Hospital and Medical Device Threat Taxonomy” by Jonathan Brett Crawley, ostering.com, licensed under CC BY-NC-ND 4.0.
These additional permissions are given alongside the licence. They add to what the licence allows and do not take anything away from it.
Version
| Version | Date | Change |
|---|---|---|
| 1.0 | 4 November 2026 | First published as reference pages, with PDF, Excel, SKOS and STIX downloads. References are stable identifiers. |
Corrections, missing threats and worked examples are welcome: reach out to me on LinkedIn. Changes are logged here.